
Ropeginterferon Alfa-2b Effective in Phase 3 Essential Thrombocythemia Trial

By Jordyn Sava
Fact checked by Jason Broderick

The SURPASS-ET trial (NCT04285086), evaluating ropeginterferon alfa-2b (Besremi) in patients with essential thrombocythemia (ET), has achieved its primary endpoint, demonstrating a durable clinical response as defined by modified European Leukemia Net (ELN) criteria.1

In the intent-to-treat (ITT) population, 42.9% (39/91) of patients treated with ropeginterferon alfa-2b had durable responses at 9 and 12 months vs 6.0% (5/83) of patients enrolled in the comparator arm who were treated with anagrelide (Agrylin) (P =.0001).

For the secondary end point, the JAK2 V617F allele burden decreased from 33.7% to 25.3% (-8.4%) in the ropeginterferon alfa-2b group over 12 months, compared with a reduction from 39.7% to 37.3% (-2.4%) in the anagrelide group. These findings indicate that ropeginterferon alfa-2b may provide a more pronounced effect on mitigating the underlying disease pathology relative to anagrelide.

“We are extremely proud of the SURPASS-ET phase 3 study outcome, which shows the potential of [ropeginterferon alfa-2b] as an important new treatment option for patients with ET, a rare blood cancer that drastically increases the risk of heart attack or stroke,” said Ko-Chung Lin, PhD, founder and chief executive officer of PharmaEssentia, in a press release. “The data highlight the broad potential to apply our innovative monopegylated, long-acting interferon technology as a significant step forward for treating ET, and potentially other myeloproliferative neoplasms, with non-chemotherapy treatments.”

For safety, ropeginterferon alfa-2b did not lead to any treatment-related serious adverse events. Overall, the agent had a manageable safety profile.

Full trial results, including additional pharmacokinetics and biomarker data, are expected to be presented at a later date.

“The results of the SURPASS-ET trial are significant,” said Albert Qin, MD, PhD, chief medical officer, PharmaEssentia, in a press release. “ET is a challenging condition associated with symptoms and risks of thrombosis and disease progression. These encouraging results highlight the potential of [ropeginterferon alfa-2b] to provide an effective and tolerable new treatment option that we believe could provide a substantial clinical benefit for patients with ET. We plan to submit these results to the FDA and other regulatory agencies as soon as possible in hopes of providing this potential new treatment option to patients with ET.”
Read more

Ruxolitinib Combinations in MPNs: Updates From ASH

January 8, 2025

Author(s): Mary Caffrey

Following its approval in 2011 for myelofibrosis (MF), ruxolitinib (Jakafi, Incyte) became the backbone of treatment for MF and later for polycythemia vera (PV), 2 of the 3 common myeloproliferative neoplasms (MPNs).

But although ruxolitinib improves survival outcomes and quality of life, some patients may not respond to therapy, while others may stop due to genetic mutations, disease progression, or other factors. For years now, investigators have been studying the Janus kinase (JAK) inhibitor in combination with other drugs, both in first-line treatment and refractory disease. Abstracts and oral presentations at the recent 66th American Society of Hematology (ASH) Annual Meeting and Exposition, held December 7-10, 2024, in San Diego, California, offered updates on several combinations in the pipeline:

MANIFEST-2. Previous results from this phase 3 study (NCT04603495) of pelabresib, a selective bromodoman and extraterminal domain (BET) inhibitor, with ruxolitinib show it met its primary end point; in patients with MF not treated with a JAK inhibitor, a statistically significant higher proportion showed at least 35% reduction in spleen volume from baseline at week 24 with the combination vs ruxolitinib and placebo. Results presented at ASH showed those results were maintained after a median follow-up of 72 weeks, with a 48-week response rate of 57.0% for the combination vs 37.5% for ruxolitinib and placebo. An improvement in the Myelofibrosis Symptom Assessment Form total symptom score (TSS) by at least 50% was seen in 45.3% of patients receiving the combination vs 39.4% in the placebo group.1

Bomedemstat. An abstract at ASH reported on an ongoing phase 2 study (NCT05569538) involving bomedemstat combined with ruxolitinib in patients with advanced MF.2 Bomedemstat is an irreversible inhibitor of lysine-specific demethylase 1 (LSD1), which plays a role in gene regulation; blocking this enzyme alters cell differentiation and growth. In August 2024, Merck announced the second phase 3 trial of bomedemastat in another MPN, essential thrombocythemia (ET).

The abstract authors noted that about 50% of patients with MF stop ruxolitinib after 3 years, mostly due to disease progression or cytopenia; median OS after discontinuation is 14 months.2 LSD1, they write, is “critical for self-renewal” of cancerous stem cells, and has shown promise as a single agent. This study reported on 2 cohorts: Cohort A had a suboptimal response to ruxolitinib, and cohort B patients had MF and were treatment naive. Patients in cohort A remained on the entry dose of ruxolitinib while cohort B started 10 mg twice per day; all patients received a starting dose of 0.4 mg/kg/day of bomedemstat. Dose adjustments were permitted every 4 weeks to achieve an optimal platelet count; downward titrations were done at any time for safety reasons. After a median of 61.7 weeks, in 40 evaluable patients, at week 24, 11 patients had at least a 50% improvement in TSS, with 25.9% in cohort A and 30.7% in cohort B; 17.5% had at least 35% spleen volume reduction, with 7.4% in cohort A and 38.5% in cohort B; and 50% of patients had stable or improved hemoglobin (51.9% in cohort A and 46.3% in cohort B). There were no safety signals or deaths related to the drug, the authors said.2

Read more

Baseline Basophilia Associated With Aggressive MPN and Poor Outcomes

A more aggressive disease phenotype and poorer clinical outcomes were associated with higher baseline basophil levels among patients with myeloproliferative neoplasms (MPNs), according to the results of a retrospective study published in the American Journal of Hematology.

In the study, researchers analyzed data from 195 patients who were diagnosed with an MPN between 2008 and 2019 at a single center. Cases of chronic myeloid leukemia, chronic eosinophilic leukemia, and chronic neutrophilic leukemia were excluded. Basophilia was defined as a relative or absolute increase in peripheral blood or bone marrow aspirate within 6 months of the patient’s first diagnostic biopsy.

Of the 195 patients, 40.5% had essential thrombocythemia (ET), 23.1% had overt fibrotic phase primary myelofibrosis (PMF), 10.8% had post-ET myelofibrosis (MF), 8.2% had pre-fibrotic PMF, 8.2% had MPN-unclassifiable (MPN-U), 7.2% had polycythemia vera (PV), and 2.1% had post-PV MF.

Basophilia were present among 22% of patients. The lowest level of basophilia was present among patients with ET and PV at 8% compared with 35% among patients with pre-PMF, F-PMF, post-ET MF, post-PV MF, or MPN-U (P <.0001). There were 9% of patients who demonstrated basophilia in the bone marrow, but not the blood.

Of the patients without basophilia at baseline, researchers found that 12% developed basophilia within a median of 19.6 months after diagnosis. Older age (P <.001), higher white blood cell count (P <.001), higher reticulin grade (P =.0007), lower hemoglobin levels (P =.01), and lower platelet counts (P <.001) were significantly associated with basophilia.

Read more

Understanding Thrombocytosis in MPN Patients: What You Need to Know

For patients living with myeloproliferative neoplasms (MPNs), the term “thrombocytosis” often arises. While thrombocytosis—an elevated platelet count—is a hallmark of some MPNs like essential thrombocythemia (ET), it can also appear in other forms of MPNs or even due to unrelated secondary causes. Understanding the different contexts in which thrombocytosis occurs is key to effective management and improving quality of life.

Thrombocytosis in MPNs: A Common Feature

1. Essential Thrombocythemia (ET)

  • Primary Cause of Thrombocytosis: In ET, the overproduction of platelets is driven by genetic mutations such as JAK2, CALR, or MPL in the stem cells of the bone marrow.
  • Platelet Levels: Platelet counts in ET are persistently elevated, often exceeding 450,000/μL, and can reach over 1,000,000/μL.
  • Risk of Complications: ET-associated thrombocytosis increases the risk of blood clots (thrombosis) and bleeding due to dysfunctional platelets.

2. Polycythemia Vera (PV)

  • Secondary Thrombocytosis: PV primarily involves elevated red blood cell counts, but platelet counts are often high as well. This occurs because of the overactivity of the bone marrow, commonly linked to the JAK2 mutation.
  • Complications: In PV, elevated platelets further amplify the risk of clotting, especially when combined with high red blood cell counts.

3. Myelofibrosis (MF)

  • Variable Platelet Counts: In early stages of MF, thrombocytosis may occur due to hyperactive bone marrow. However, as the disease progresses and fibrosis (scarring) of the bone marrow develops, platelet counts often drop (thrombocytopenia).
  • Implications: Elevated platelets in early MF contribute to the overall risk of thrombosis but are usually less prominent than in ET or PV.

Thrombocytosis in MPNs vs. Reactive Thrombocytosis

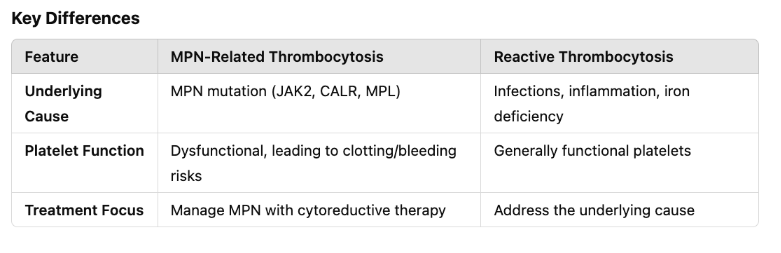
MPN patients may also develop reactive thrombocytosis, where platelet levels rise due to an external trigger rather than the disease itself. This is important to differentiate, as the treatment approach varies.

Causes of Reactive Thrombocytosis in MPN Patients:

  • Infection: Common colds, bacterial infections, or systemic inflammation.
  • Iron Deficiency: Iron depletion, often seen in PV due to phlebotomy or blood loss, can elevate platelet counts.
  • Surgery or Trauma: Any significant physical stress can temporarily increase platelet production.
  • Inflammatory Conditions: Co-existing autoimmune diseases or inflammatory processes.

Managing Thrombocytosis in MPN Patients

For MPN patients, managing thrombocytosis involves addressing both the underlying condition and associated risks:

1. Medications to Control Platelet Levels

  • Low-Dose Aspirin: Reduces the risk of clotting in patients with high platelet counts and cardiovascular risks.
  • Cytoreductive Therapy: Drugs like hydroxyurea or anagrelide may be prescribed to reduce platelet counts in high-risk patients.
  • JAK Inhibitors: For conditions like PV or MF with thrombocytosis, drugs like ruxolitinib target the underlying JAK2 pathway.

2. Monitoring and Prevention

  • Regular Blood Tests: Monitoring platelet counts and clotting markers is crucial.
  • Lifestyle Modifications: Staying active, avoiding smoking, and maintaining a healthy weight can help reduce clotting risks.
  • Avoiding Triggers: Identifying and managing secondary causes like iron deficiency or inflammation can prevent exacerbation.

3. Managing Complications

  • Clotting Risks: Thrombocytosis in MPNs increases the risk of strokes, heart attacks, and deep vein thrombosis (DVT). Prompt treatment of symptoms like chest pain, shortness of breath, or limb swelling is essential.
  • Bleeding Risks: Paradoxically, MPN patients with thrombocytosis may experience bleeding due to abnormal platelet function, such as nosebleeds, gum bleeding, or gastrointestinal bleeding. Report unusual bleeding to your healthcare provider immediately.

Living with Thrombocytosis as an MPN Patient

Thrombocytosis in the context of MPNs requires long-term management, but there are steps you can take to improve your quality of life:

  • Stay Informed: Learn about your specific MPN and its implications for thrombocytosis.
  • Build a Support Network: MPNs are rare conditions. Connecting with support groups or online communities can provide emotional support and practical advice.
  • Communicate with Your Care Team: Keep an open dialogue with your hematologist, and don’t hesitate to ask about treatment options, clinical trials, or lifestyle recommendations.

Thrombocytosis in MPN patients is more than just a high platelet count—it’s a complex condition with significant implications for your health. Understanding the nuances of your condition is essential for effective management, whether it’s caused by essential thrombocythemia, polycythemia vera, or reactive triggers. By working closely with your healthcare team and staying proactive in your care, you can navigate the challenges of thrombocytosis and live a fuller, healthier life.

A Commitment to New Therapies for MPN Despite Scientific Challenges

January 2, 2025

Author(s): Darlene Dobkowski, MA

Fact checked by: Alex Biese

A researcher discussed the evolving understanding of myeloproliferative neoplasms (MPNs), from their initial classification to their potential for progression, and emphasized the scientific community’s commitment to developing new therapies despite the inherent challenges of research.

John Crispino, director of the division of experimental hematology at St. Jude Children’s Research Hospital in Memphis, Tennessee, was recognized at the CURE MPN Heroes event for his dedication to the community both through his scientific breakthroughs and his advisory role for the MPN Research Foundation.

CURE also spoke with Crispino about what he has learned about patients with MPNs and the research around the condition over his years in the field. One of the things he mentioned was the disease’s transition from a myeloproliferative disorder to a myeloproliferative neoplasm. In particular, the World Health Organization (WHO) changed the classification of these conditions to MPNs to reflect the understanding that these conditions are a type of cancer.

Read more

Q&A: Transforming MPN Care by Aligning Research With Patient-Centered Outcomes

December 26, 2024

Physician’s Weekly (PW) met with John O. Mascarenhas, MD, and Kapila Viges to learn how the latest research impacts care for patients with myeloproliferative neoplasms (MPN).

PW: What do you see as the most beneficial of all the combinations that are being explored right now?

Ms. Viges: It’s important to remember that options matter for patients. In myelofibrosis and MPN, more broadly, these chronic diseases, patients live for decades in relatively stable health. But knowing that there are options over time if something either stops working or their disease progresses, knowing that they can sequence through a few more options and maybe even some newer combinations that are interesting, brings a lot of hope and promise for patients and gives them some comfort as they navigate their journey through their disease.

Dr. Mascarenhas: The key to treating myelofibrosis is that you need options to tailor the therapy. It’s not one treatment fits all. So, whether it’s a monotherapy, a combination, or when to switch, each agent to pick is individualized for the patient. The more options we have as physicians, the more likely we can tailor and optimize a treatment for an individual.

Ms. Viges: That’s our motto—options matter. We at MPN Research Foundation recently surveyed 676 patients to learn their treatment goals. Of these, 50% said improved quality of life. More specifically, 40% said relief from symptoms is their primary goal. Patients value the options coming online, the combinations, and how we measure and manage symptoms.

Dr. Mascarenhas: Symptoms are complex and sometimes hard to measure. It’s hard to measure the actual or absolute benefit of a given therapy or combinations with symptoms. So, it’s been an area in our field for drug development where we’re trying to figure out the best way to capture that benefit for any individual patient because some patients may benefit to greater degrees than others, and not all therapies are ideal for any given patient. It is a complex world that we’re living in in terms of trying to navigate this. But, patients are symptomatic, and they want to feel better. Physicians want to make patients feel better, but we also want to extend survival with good symptomatology. So it’s a mixed picture. For some patients, the symptoms may be systemic or cytokine symptoms.

Do you think trials will continue considering additional endpoints or exploring more markers?

Dr. Mascarenhas: One of the fundamental deficiencies in our field is that we currently measure spleen and symptom reduction as our primary endpoints for clinical trials because we started the field with JAK inhibitors. They don’t do it for everyone perfectly and don’t always maintain it indefinitely for every patient. So that’s some of the nuances, but we are moving into an area where we’re looking now at therapeutics that might be able to change the natural disease history. The problem with the trials we design often is that we don’t follow patients because you need a lot of patients; you need a lot of power to do it.

Statistically, we don’t always follow them to the point where we can confirm survival. So we are in a desperate search for surrogate markers that you can look at earlier on, whether it’s spleen reduction or symptom burden even, or bone marrow fibrosis reduction, driver mutation reduction, cytokine reductions, things that you can measure maybe at a six month period that may correlate and associate down the line with a survival benefit. It’s key for us as investigators and the research foundation to figure out how we do that as a group so that we’re not at the stumbling block where we’re trying to understand what we are achieving.

Read more

Options for MPN Treatment Are Expanding Rapidly With More on the Horizon

December 24, 2024

Author(s): Laura Joszt, MA, Luke Halpern

The past few years have been an exciting time in myeloproliferative neoplasms (MPNs) with new treatments providing new options for patients and additional products in the pipeline that explore new mechanisms of action, explained Firas El Chaer, MD, associate professor of medicine, University of Virginia School of Medicine. At the American Society of Hematology annual meeting, El Chaer had presented research and been a coauthor on abstracts related to treatment for myeloproliferative neoplasms.

He discussed how MPNs are diagnosed, the current treatment landscape, and promising new therapies in the pipeline. When diagnosing for MPNs, particularly for myelofibrosis, a bone marrow biopsy is needed, but the challenge is that this can be “patchy,” he explained, and the amount of fibrosis present in the particular part of the bone marrow that is biopsied is what is relied upon to make the diagnosis.

The good news is that the approval of many new Janus kinase inhibitors has changed the treatment landscape of myelofibrosis dramatically in the last few years, El Chaer said, which has provided patients with additional options for treatment. In addition, there are new mechanisms of action that can improve anemia in this patient population.

“I’m very excited that currently we’re thinking about combination therapies,” he said, to improve anemia or that potentially have a disease-modifying capability. “Our field is expanding very quickly.”

He highlighted some of the new mechanisms of action being studied in myeloproliferative neoplasms, such as bromodomain molecules and TGF-β agonists, which can potentially be helpful for anemia and this patient population. He had presented phase 1/2 data on nuvisertib, or TP-3654, which is a highly selective PIM1 kinase inhibitor that has reduced spleen size and bone marrow fibrosis either alone or in combination with ruxolitinib. Nuvisertib has minimal cytopenia side effect and can be combined with other molecules for treatment. Currently, enrollment is ongoing in 3 arms of the study (NCT04176198) to continue to evaluate nuvisertib as a monotherapy and in combination with ruxolitinib and momelotinib.

Read more

HMGA2 overexpression with specific chromosomal abnormalities predominate in CALR and ASXL1 mutated myelofibrosis

Shivani Handa, Christoph Schaniel, Joseph Tripodi, Daiva Ahire, Md. Babu Mia, Sophie Klingborg, Douglas Tremblay, Bridget K. Marcellino, Ronald Hoffman & Vesna Najfeld

December 23, 2024

Abstract

Although multiple genetic events are thought to play a role in promoting progression of the myeloproliferative neoplasms (MPN), the individual events that are associated with the development of more aggressive disease phenotypes remain poorly defined. Here, we report that novel genomic deletions at chromosome 12q14.3, as detected by a high-resolution array comparative genomic hybridization plus single nucleotide polymorphisms platform, occur in 11% of MPN patients with myelofibrosis (MF) and MPN-accelerated/blast phase (AP/BP) but was not detected in patients with polycythemia vera or essential thrombocythemia. These 12q14.3 deletions resulted in the loss of most of the non-coding region of exon 5 and MIRLET7 binding sites in the 3’UTR of the high mobility group AT hook 2 (HMGA2), which negatively regulate HMGA2 expression. These acquired 12q14.3 deletions were predominately detected in MF patients with CALR and ASXL1 co-mutations and led to a greater degree of HMGA2 transcript overexpression, independent of the presence of an ASXL1 mutation. Patients with 12q structural abnormalities involving HMGA2 exhibited a more aggressive clinical course, with a higher frequency of MPN-AP/BP evolution. These findings indicate that HMGA2 overexpression associated with genomic deletion of its 3’UTR region is a newly recognized genetic event that contributes to MPN progression.

Read more


Bromodomain and BET Inhibitor INCB057643 Shows Benefit for Patients With Myelofibrosis

12/19/24

Emily Estrada

According to research presented by Justin Watts, MD, Sylvester Cancer Center Institute, University of Miami, Miami, Florida at the 2024 American Society of Hematology (ASH) Annual Meeting & Exposition in San Diego, California, INCB057643 may improve patient outcomes in the treatment of hematologic malignancies, including myelofibrosis (MF).

A small-molecular bromodomain and extra-terminal BET protein inhibitor, INCB057643, has shown safety and tolerability as monotherapy and combination with Janus kinase (JAK) 1 and 2 inhibitors among patients with MF in previous phases of the ongoing phase 1/2 clinical trial. In this dose-escalation and expansion portion of the trial, the dose of INCB057643 in patients with MF receiving monotherapy was increased from 4mg to 12mg and for patients with MF who had an inadequate response to ruxolitinib, combination therapy dosage was increased from 4mg to total maximum dosage.

The primary end points were safety and tolerability, as well as dose-limiting toxicities of INCB057643 at 24 weeks. The secondary end points included spleen volume reduction greater than 35% from baseline (SVR35), symptom reduction by greater than 50% from baseline via MPN-Symptom Assessment Form (TSS50), and anemia response of a hemoglobin increase at least 1.5 g/dL from baseline in patients that were not receiving transfusions or transfusion-free for at least 12 weeks for patients dependent on transfusions at baseline.

Patients with relapsed/refractory MF (84.1%%), essential thrombocythemia ([ET]; 4.5%), myelodysplastic syndromes (MDS), or myeloproliferative neoplasm (MPN) syndromes (11.4%). were included in the study. In total, 18 patients were treated with a monotherapy dose escalation and 10 patients received dose expansion. Combination therapy dose escalation was received by 16 patients whose median age was 71 years and whose median ruxolitinib dose was 22.4mg per day. The median duration of INCB057643 exposure was 195.5 days for patients in the monotherapy dose-escalation cohort and 139.0 days for patients in the dose-expansion cohort. As for patients who were in the combination therapy dose-escalation cohort, median INCB057643 exposure was 194.0  days.

At 24 weeks, 3 out of 16 patients who received monotherapy achieved SVR35 and 5 out of 14 achieved TSS50 with any dose of INCB057643, of which 3 received a dose of at least 10 mg. During any time of treatment, improvements in spleen volume and TSS50 best response were demonstrated by 13/19 and 12/15 patients, respectively. Among patients who received combination therapy of INCB057643 and ruxolitinib, 3 out of 12 patients achieved SVR35 and 6 out of 11 achieved TSS50 at any combo dose. Improvements were seen at any time during treatment for both SVR35 and TSS50 in 13 out of 16 and 10 out of 15 patients, respectively. Of patients not dependent on blood transfusions, an anemia response was demonstrated by 3 patients in both the monotherapy and the combination group. Additionally, of 6 patients who were blood transfusion dependent at BL, 2 achieved transfusion independence.

Read more

Transforming Care With Collaboration, Individualized Treatment, and Novel Therapies

Author(s): Laura Joszt, MA

December 20, 2024

Patients with chronic hematologic malignancies are living for decades, especially with new treatments, making it an important time to shape value-based treatments being offered to these patients, said Jennifer Vaughn, MD, during a fireside chat at the Cleveland Regional Institute of Value-Based Medicine (IVBM) event hosted by The American Journal of Managed Care.

Vaughn, a hematology specialist specializing in myelodysplastic syndromes at The Ohio State University, was joined by Akriti Jain, MD, a hematologist at Cleveland Clinic, to discuss quality care initiatives in rare hematological disorders.

With myelofibrosis, for example, the disease can be very high risk or very low risk, and there have been recently approved Janus kinase (JAK) inhibitors to treat the disease, with more coming. There are 4 approved JAK inhibitors1: ruxolitinib (Jakafi), fedratinib (Inrebic), pacritinib (Vonjo), and momelotinib (Ojjaara). With multiple treatments available, it’s important to understand the individual patient’s symptoms to choose the most effective therapy.

“One of the main things that we talk about these days is individualizing care, right? Not every patient is the same,” Jain said. “So, when I see a patient with myelofibrosis in clinic, the first question is: What are they presenting with?” If a patient has the typical symptoms of myeloproliferative neoplasms (MPNs), a JAK inhibitor is probably the right way to go, she said. If they don’t have those symptoms but they have anemia or thrombocytopenia, then a little more investigation is needed.In the polycythemia vera space, there are also a number of agents now available that can lead to a reduced risk of progression in the future. Vaughn explained that when she sees a younger patient, they now have the opportunity to take aspirin and go to the doctor for routine phlebotomies and labs or a treatment that they can manage and can limit time away from work and their kids.

“That’s been, now, a really interesting discussion in that patient population for me, because there are many of my patients who have actually opted to go on therapy,” she said. “We all think of phlebotomy as this very low-risk, easy [procedure] to undergo, but phlebotomy is just a real…pain for them. They can’t spend the time away.”

She added that “time toxicity” is being considered more and more, which is a way to evaluate how much time patients spend having to engage in their health care treatments.

Read more